Research and clinical practice
Psychedelics in mental health: what the evidence says
In psychedelic-assisted therapy, a psychedelic substance that alters consciousness in a distinctive way, unlike usual psychiatric medication, is given in a small number of sessions, with preparation, support and psychological integration. It is an active field of research, with early results in mental health.

In brief
Under study in mental health: psychedelic therapy for depression, notably treatment-resistant depression, and for post-traumatic stress disorder, addictions, palliative care and end-of-life anxiety.
What does “psychedelic” mean?
- psyche
- mind
- dēloun
- to make manifest or visible
- psychedelic
- a word coined by the psychiatrist Humphry Osmond in the 1950s1
The word was proposed by the psychiatrist Humphry Osmond, in a scientific paper in 1957.1 It describes substances that make more manifest aspects of the mind less accessible in daily life, such as memories and emotions.
Read more
The original idea was to describe very particular substances, capable of producing profound changes in perception, emotion, thought and the experience of self. Osmond introduced the word in a scientific paper in 1957, as an alternative to terms that linked these substances to the imitation of psychosis.1
The name captures what makes them unique: during their effect, aspects of the mind that are less accessible in everyday life, such as memories, emotions and the way people see themselves and others, can become more manifest. It is this effect, very different from that of other medicines used in psychiatry, that lies behind the clinical and scientific interest in these substances.
Psychedelic does not refer to a single class of drugs
The substances studied differ in mechanism, duration and effects.2
Classic psychedelics
Psilocybin · DMT · LSD
Markedly change perception, thinking and emotion; act mainly on serotonin.
Entactogens
MDMA
Effects mainly on emotions and on relating to others.
Dissociatives
Ketamine and esketamine
Anaesthetics that change the perception of the body, space and time; act on glutamate.
Read more
Classic psychedelics. They act mainly through the serotonergic system, particularly 5-HT2A receptors, and can produce marked changes in perception, thought, emotion and the experience of self.
Entactogens. They produce a profile distinct from classic psychedelics, with particularly marked effects on emotional and interpersonal processing.
Dissociatives. They act mainly through the glutamate system and can alter the perception of the body, space and time, and the experience of the self.
From early research to the return to clinical investigation
- 1950–1960
Research begins with LSD, psilocybin and other substances.
- Following decades
Interruption due to legal, social and scientific changes.
- From the 1990s
Research resumes, with current methods.
- Today
Clinical research with several substances; dissociatives already have a place in psychiatry.
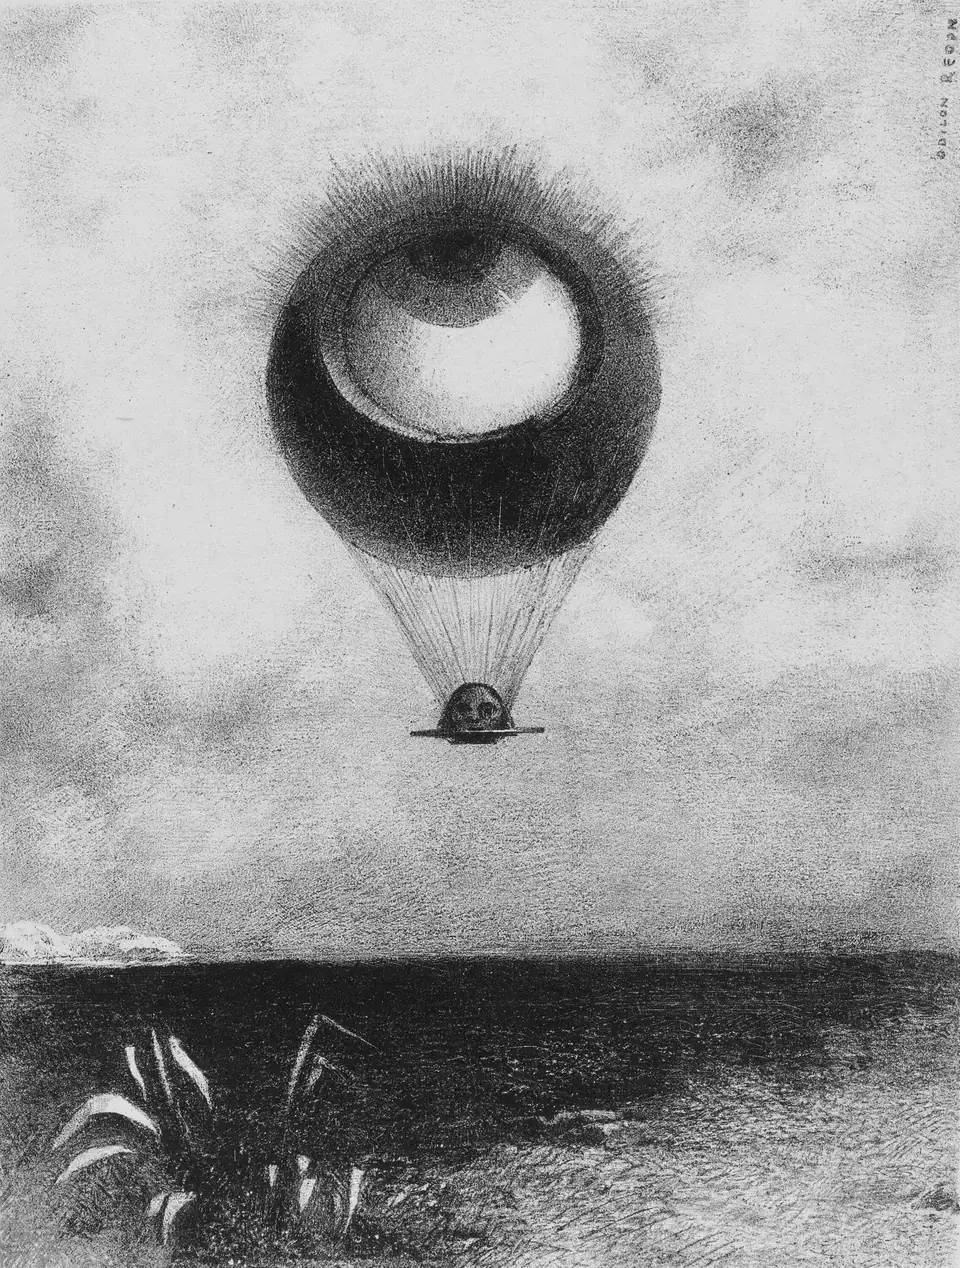
Long before clinical research, perception and the inner world were already central themes of Symbolist art. Redon dedicated this lithograph to Edgar Allan Poe.
Odilon Redon, The Eye, Like a Strange Balloon, Mounts toward Infinity, plate I of To Edgar Poe, 1882. Lithograph. Art Institute of Chicago. Public domain. Catalogue record (external site)
A different therapeutic model
Conventional psychiatric medicines and psychedelic-assisted therapy follow different logics.
Conventional psychiatric medicines
Regular, continuous use; the effect is pharmacological.
Psychedelic-assisted therapy
A few sessions; the experience during the effect is part of the treatment.
| Conventional psychiatric medicines | Psychedelic-assisted therapy | |
|---|---|---|
| How it is taken | Regularly, usually daily | A few sessions with the substance |
| Where | At home | In a clinical setting, with support |
| Role of the experience | Not the focus of treatment | Part of the therapeutic process |
| Psychological support | Psychotherapy may be added | Preparation and integration are built in |
| Duration | Months or years | A time-limited programme |
| In Portugal | Authorised medicines | Psilocybin, MDMA, LSD and DMT: only in clinical trials |
See the full table
| Difference | Conventional psychiatric medicines | Psychedelic-assisted therapy |
|---|---|---|
| How it is taken | Taken regularly, usually daily, throughout treatment. | A limited number of sessions with the substance, in many research protocols. |
| Where | At home, by the person themselves. | In a controlled clinical setting, with professional support throughout the effect. |
| Role of the experience | The effect sought is pharmacological and continuous; the subjective experience is not the focus of treatment. | The experience during the acute effect is part of the therapeutic process itself. |
| Psychological support | Psychotherapy may be added, but it is not part of the medicine. | It is part of the model: preparation before the session and integration afterwards. |
| Duration | Months or years of continuous use, with a planned reduction when appropriate. | A time-limited programme: assessment, preparation, sessions and follow-up. |
| Framework in Portugal | Medicines authorised for defined indications. | Psilocybin, MDMA, LSD and DMT: access through clinical trials. |
More than administering a substance
The substance is given within a structured clinical process, which varies with the substance, the indication and the setting.
- Assessment
- Diagnosis and previous treatments
- Medication and medical history
- Risks and goals
- Preparation
- What to expect from the session
- How to handle difficult experiences
- Session
- The substance under controlled conditions
- Professional support
- Follow-up
- Reviewing the experience
- Integration, in some models
Read more
Assessment. Diagnosis, previous treatments, current medication, medical and psychiatric history, risk factors and therapeutic goals.
Preparation. Information about the procedure, expected effects, possible difficult experiences, expectations and strategies for navigating the session.
Session. Administration of the substance under controlled conditions, with professional support appropriate to the protocol used.
Follow-up. Subsequent review of the experience and its clinical meaning. In some models, this includes dedicated integration sessions.
Areas currently under investigation
- 01Depressive disordersIncluding forms resistant to treatment.
- 02Post-traumatic stressAmong the most studied areas.
- 03Substance useStudies across different addictions.
- 04Palliative care and end-of-life anxietyEffects on anxiety, depression and existential distress.
Other areas under investigation
- Obsessive-compulsive disorderPsilocybin: after a first small study, a 2026 randomised trial showed a reduction in obsessive symptoms.9,10
- Smoking cessationPsilocybin with cognitive behavioural therapy: in a pilot randomised trial, more people stopped smoking than with a nicotine patch.11
- Alcohol use disorderPsilocybin with psychotherapy: fewer heavy drinking days than with placebo, in a randomised controlled trial.12
- Anorexia nervosaPsilocybin: an early study, without a control group, focused on safety and feasibility.13
- Trauma and couple relationshipsMDMA combined with conjoint couple therapy: an early study, without a control group, in post-traumatic stress disorder.14
- Social anxiety in autistic adultsMDMA with psychotherapy: a small placebo-controlled pilot trial.15
Each combination of substance, diagnosis and protocol has its own level of evidence.3,4
Psilocybin, MDMA, LSD and DMT are in clinical development and do not yet have a marketing authorisation. In Portugal, clinical access to these substances is through clinical trials; in other EU countries there are already exceptional, restricted access routes (checked on 8 October 2026).8 The legal position of each substance in Portugal is summarised on KETAMED's Psychedelics in Portugal (opens in a new tab) page, and that of other countries on Psychedelics worldwide (opens in a new tab).
Not everyone is a suitable candidate
A prior clinical assessment is essential. Psychiatric and medical history, cardiovascular disease and medication can change the risk; the assessment exists so that treatment can be carried out safely.
Training Pathway in Psychedelic Therapy
Pedro Zuzarte
- 2006First contact with clinical research on psychedelics during an internship at the Federal University of Santa Catarina, Brazil.
- 2014–2018Training experience with Gabor Maté in Canada, focused on the integration and therapeutic context of psychedelic experiences.
- MexicoExperience supporting a therapeutic group setting with Gabor Maté in Yelapa, including a setting related to DMT.
- 2022Specialised training in Psychedelic-Assisted Therapy at the California Institute of Integral Studies (CIIS).
- 2022Set up a programme of therapy assisted by a dissociative anaesthetic with psychedelic properties at the Centro Clínico das Janelas Verdes, Ministry of Internal Affairs.
- MAPSComplementary training in MDMA-assisted therapy through the Multidisciplinary Association for Psychedelic Studies (MAPS).
- TodayDirects university training in Psychedelic Therapy at the Faculty of Medicine of the University of Lisbon.
Different molecules. Different experiences. Different evidence.
These substances differ in pharmacology, duration, experience and stage of clinical development.

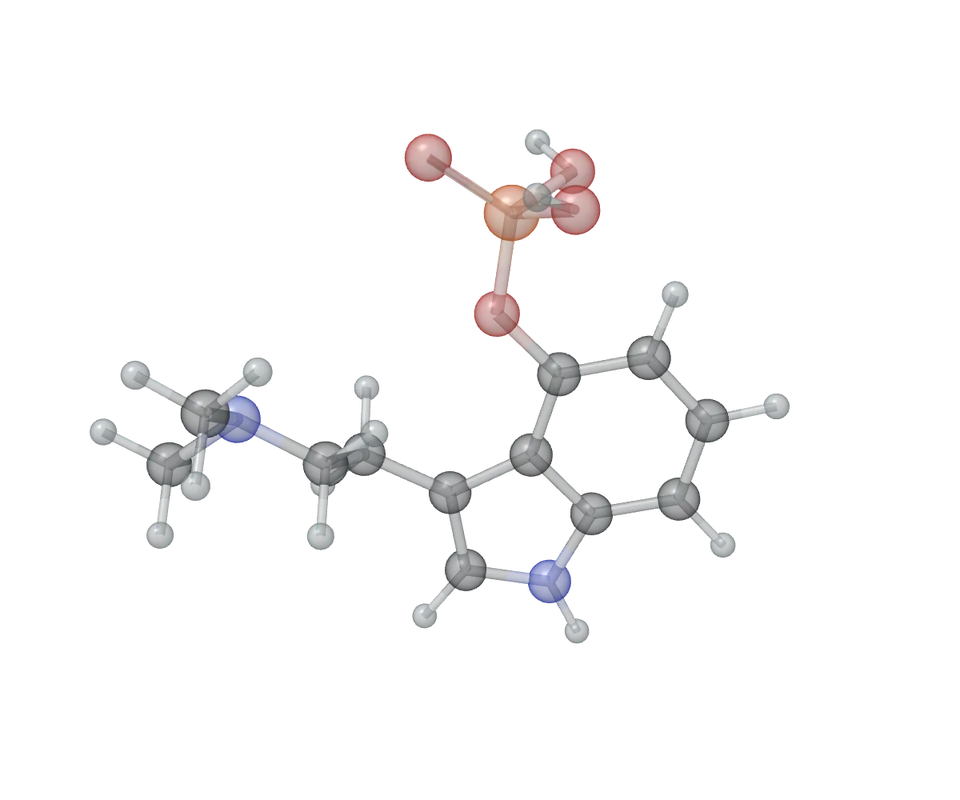
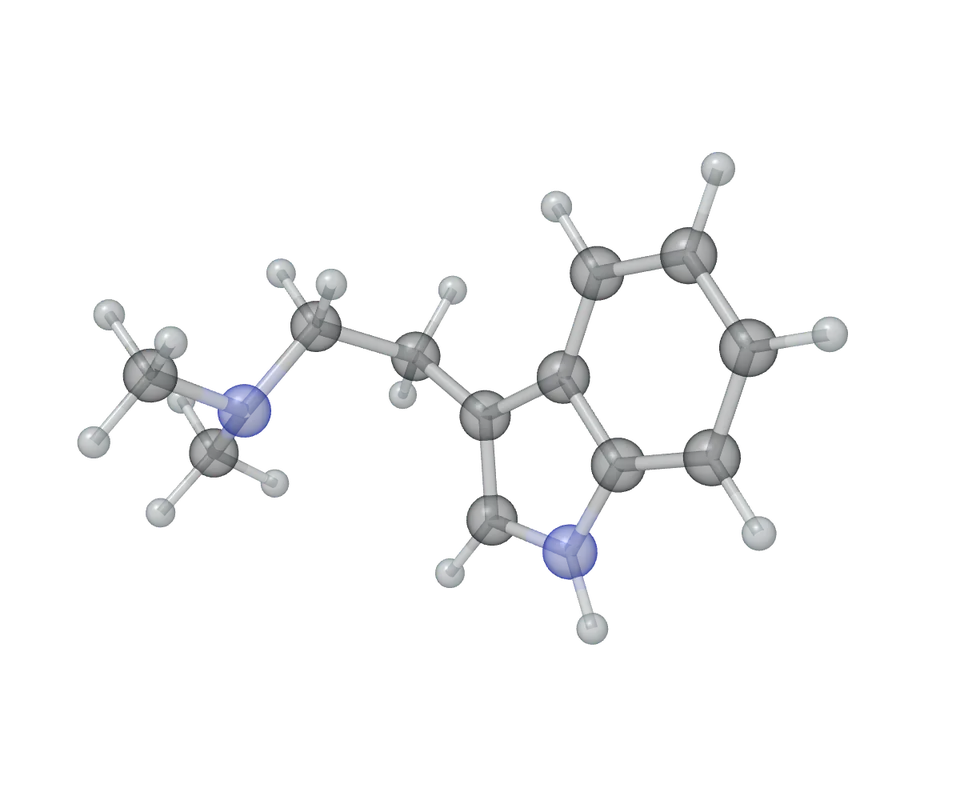
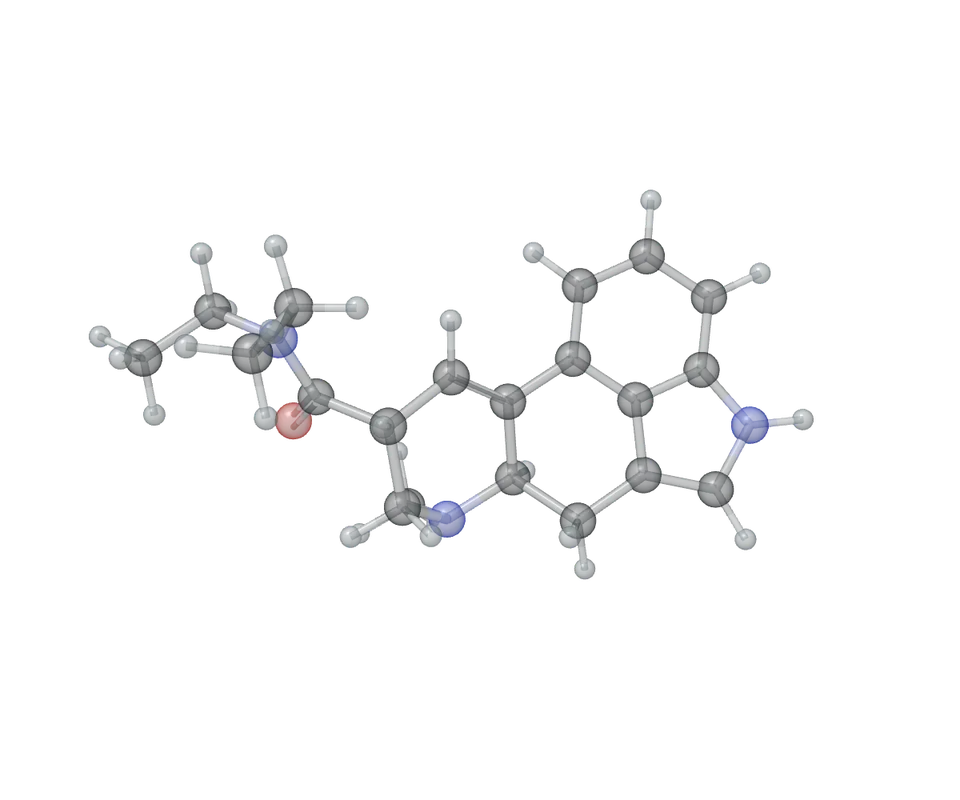
01Classic psychedelic
Psilocybin
C12H17N2O4P
- What it is
- Psilocybin is a psychedelic compound found in several species of mushrooms. In the body it is converted into psilocin, the molecule responsible for much of its psychoactive effect.
- Research
- Psilocybin is being studied mainly in depressive disorders, including treatment-resistant depression, in substance use disorders, palliative care and end-of-life anxiety.3
Read more
How it works. Psilocin acts mainly on the serotonergic system, particularly 5-HT2A receptors, producing transient changes in how different brain networks process information.
Subjective experience. There may be changes in visual and sensory perception, the experience of time, thought, emotions and the sense of identity or of separation between self and surroundings.
02Classic psychedelic
DMT
N,N-dimethyltryptamine
C12H16N2
- What it is
- DMT is a psychedelic tryptamine structurally related to other serotonergic molecules. It is also present in traditional preparations such as ayahuasca, although these represent a different pharmacological context because of the other substances they contain.
- Research
- DMT is currently being studied in experimental and clinical models, including research related to depression. Its clinical development is, however, at an earlier stage than that of some of the other substances on this page.
Read more
How it works. Its psychedelic effects are associated mainly with its action on serotonin receptors, including 5-HT2A receptors.
Subjective experience. It can produce very intense changes in perception, the experience of space and time, body image and the sense of identity. Duration varies markedly with the route of administration.
03Classic psychedelic
LSD
Lysergic acid diethylamide
C20H25N3O
- What it is
- LSD is a semi-synthetic psychedelic derived from compounds of the ergoline family. It was one of the most studied substances during the first phase of psychedelic research in the twentieth century.
- Research
- After decades of very limited clinical research, LSD is again being studied in psychiatric and experimental settings, including mood disorders and anxiety.5
Read more
How it works. Its pharmacology is complex, but its psychedelic effects depend substantially on its action on the serotonergic system and 5-HT2A receptors.
Subjective experience. It can produce intense changes in perception, thought, emotion, the experience of time and the sense of self. One feature that distinguishes it from other classic psychedelics is its generally long duration.
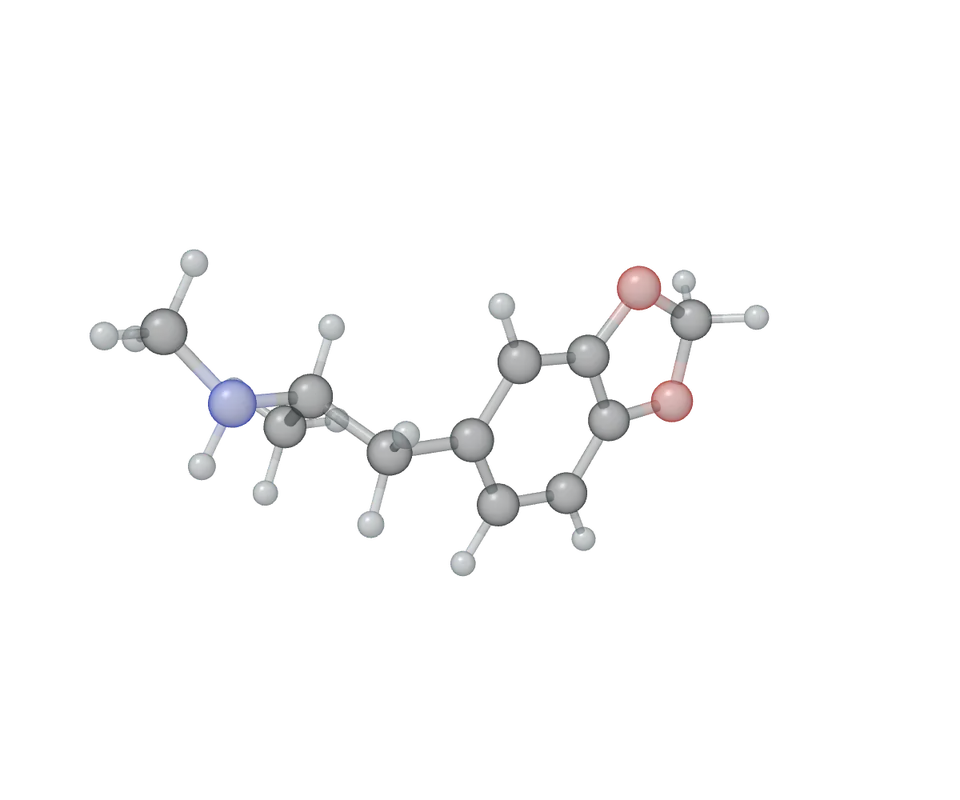
04Entactogen
MDMA
3,4-methylenedioxymethamphetamine
C11H15NO2
- What it is
- MDMA is not a classic psychedelic. It is usually classified as an entactogen because of its particular profile of emotional and interpersonal effects.
- Research
- The most developed area of clinical research with MDMA has been MDMA-assisted therapy for post-traumatic stress disorder.4
- Regulatory status
- In 2024 the FDA did not approve MDMA-assisted therapy and asked for an additional trial; it is not approved in the European Union or in Portugal.7
Read more
How it works. It markedly alters monoamine transmission, mainly serotonin but also noradrenaline and dopamine, through mechanisms different from those of classic psychedelics.
Subjective experience. It can increase feelings of interpersonal closeness and emotional openness and change how emotionally salient stimuli are processed.
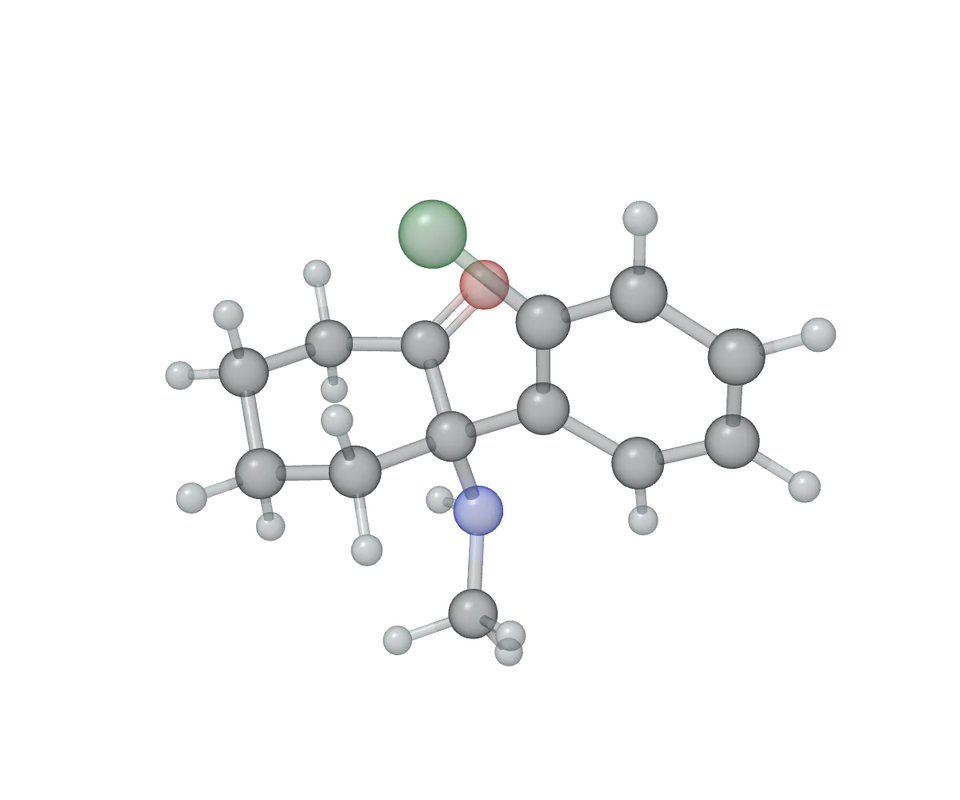
05Dissociative
Ketamine and esketamine
C13H16ClNO
- What it is
- It is a dissociative anaesthetic with psychedelic properties that has been used in medicine for several decades. This is ketamine; esketamine is one of its two mirror-image forms. At doses lower than those usually used in anaesthesia, it has shown a rapid-onset antidepressant effect in trials and has come to occupy a particular place in psychiatric research and practice.
- Safety
- It has a potential for misuse or dependence, can raise blood pressure and requires monitoring after each dose; repeated use can cause bladder toxicity.6
Read more
How it works. Its pharmacology differs from that of classic psychedelics. One of the main mechanisms involves modulation of the glutamate system through NMDA receptors, triggering downstream changes in different circuits and cellular processes.
Subjective experience. Depending on the dose and the person, there may be changes in the perception of the body, space and time, a sense of detachment from one's body or surroundings, altered consciousness and intensely introspective experiences.
By condition
Reading by clinical condition
What research shows in each condition, with the stage of each study, safety and the position in Portugal.
From research to clinical practice
In Portugal, ketamine is approved as an anaesthetic; in depression its use is off-label. Psychedelic therapy and the psychotherapies that accompany it remain under research, and further studies are still needed before a formal clinical indication. Any decision is individual, made after psychiatric assessment and with written informed consent. Esketamine nasal spray, a variant of the same molecule, is authorised in the European Union for treatment-resistant depression.6 The difference between the names is explained in the article ketamine and esketamine: what is the difference?
Anaesthetic formulation
Approved anaesthetic · off-label use
- A mixture of the two mirror-image forms of the molecule
- In trials, mostly intravenous
- Prior assessment and monitoring at every administration
Intranasal formulation
Approved in the EU since 2019 for treatment-resistant depression
- Esketamine nasal spray
- With an SSRI or SNRI antidepressant
- Under direct clinical supervision
Assessing treatment options
Suitability for treatment with dissociative anaesthetics depends on the diagnosis, previous treatments, medication and history; the first step is a medical assessment of the indication, risks and alternatives.
Key points
- In psychedelic-assisted therapy, the substance is given in a few sessions, within a clinical process.
- The substances differ greatly, in evidence and in regulation (ketamine, also spelt cetamina; esketamine).
- For psychedelic therapy in a clinical setting, see psychedelic-assisted therapy at KETAMED (opens in a new tab).
Read also
- Ketamine and esketamine treatment for treatment-resistant depression
- Treatment-resistant depression: step-by-step options
- Psilocybin and other psychedelics for depression
- MDMA-assisted therapy for post-traumatic stress disorder
- Psychedelics for anxiety: LSD and psilocybin
- Depression: symptoms, assessment and treatment
References
- Osmond H. A review of the clinical effects of psychotomimetic agents. Ann N Y Acad Sci. 1957;66(3):418–434. doi:10.1111/j.1749-6632.1957.tb40738.x · PubMed
- Nichols DE. Psychedelics. Pharmacol Rev. 2016;68(2):264–355. doi:10.1124/pr.115.011478 · PubMed
- Goodwin GM, et al. Single-dose psilocybin for a treatment-resistant episode of major depression. N Engl J Med. 2022;387(18):1637–1648. doi:10.1056/NEJMoa2206443 · PubMed
- Mitchell JM, et al. MDMA-assisted therapy for severe PTSD: a randomized, double-blind, placebo-controlled phase 3 study. Nat Med. 2021;27(6):1025–1033. doi:10.1038/s41591-021-01336-3 · PubMed
- Holze F, et al. Lysergic acid diethylamide-assisted therapy in patients with anxiety with and without a life-threatening illness: a randomized, double-blind, placebo-controlled phase II study. Biol Psychiatry. 2023;93(3):215–223. doi:10.1016/j.biopsych.2022.08.025 · PubMed
- European Medicines Agency. European public assessment report (EPAR) for the intranasal formulation authorised for adults with treatment-resistant depression; EU marketing authorisation since 18 December 2019. Official source
- Lykos Therapeutics. Announcement of the FDA complete response letter for the MDMA (midomafetamine) application for post-traumatic stress disorder. 9 August 2024. Source
- European Medicines Agency, medicines register (accessed 8 October 2026); Czech Republic, Act No. 270/2025 Coll., in force since 1 January 2026, and Government Regulation No. 552/2025 Coll. (psilocybin for restricted therapeutic use); Germany, compassionate use programme for psilocybin in treatment-resistant depression, Central Institute of Mental Health, Mannheim (press release of 31 July 2025). Act 270/2025 Coll. · CIMH Mannheim · EMA
- Moreno FA, Wiegand CB, Taitano EK, Delgado PL. Safety, tolerability, and efficacy of psilocybin in 9 patients with obsessive-compulsive disorder. J Clin Psychiatry. 2006;67(11):1735–1740. doi:10.4088/jcp.v67n1110 PubMed
- Moreno FA, Allen KE, Wiegand CB, et al. A randomized clinical trial of repeated doses of psilocybin for the treatment of obsessive-compulsive disorder. J Psychopharmacol. 2026;40(5):837–849. doi:10.1177/02698811261424214 PubMed
- Johnson MW, Naudé GP, Hendricks PS, Garcia-Romeu A. Psilocybin or nicotine patch for smoking cessation: a pilot randomized clinical trial. JAMA Netw Open. 2026;9(3):e260972. doi:10.1001/jamanetworkopen.2026.0972 PubMed
- Bogenschutz MP, Ross S, Bhatt S, et al. Percentage of heavy drinking days following psilocybin-assisted psychotherapy vs placebo in the treatment of adult patients with alcohol use disorder: a randomized clinical trial. JAMA Psychiatry. 2022;79(10):953–962. doi:10.1001/jamapsychiatry.2022.2096 PubMed
- Peck SK, Shao S, Gruen T, et al. Psilocybin therapy for females with anorexia nervosa: a phase 1, open-label feasibility study. Nat Med. 2023;29(8):1947–1953. doi:10.1038/s41591-023-02455-9 PubMed
- Monson CM, Wagner AC, Mithoefer AT, et al. MDMA-facilitated cognitive-behavioural conjoint therapy for posttraumatic stress disorder: an uncontrolled trial. Eur J Psychotraumatol. 2020;11(1):1840123. doi:10.1080/20008198.2020.1840123 PubMed
- Danforth AL, Grob CS, Struble C, et al. Reduction in social anxiety after MDMA-assisted psychotherapy with autistic adults: a randomized, double-blind, placebo-controlled pilot study. Psychopharmacology (Berl). 2018;235(11):3137–3148. doi:10.1007/s00213-018-5010-9 PubMed
Written and reviewed by Pedro Zuzarte, psychiatrist · Last reviewed:
Educational health information, prepared taking into account the position of the College of Psychiatry of the Portuguese Medical Association on the use of psychedelics (CEP-2023-R-02). It is not advertising for medicines nor a treatment recommendation, and it does not replace a medical consultation.
A psychiatric assessment can be the first step.
If you are looking for psychedelic therapy, KETAMED is the clinic dedicated to this field.
Discover KETAMED (opens in a new tab)
Follow KETAMED: Instagram (opens in a new tab) · Facebook (opens in a new tab)