Cognitive difficulties: memory and attention
Cognitive difficulties, such as forgetfulness, difficulty concentrating or a sense of slowed thinking, have many causes, several of them treatable, and do not always mean dementia. The psychiatric assessment starts by distinguishing between them, so that what is treatable is identified and treated early.
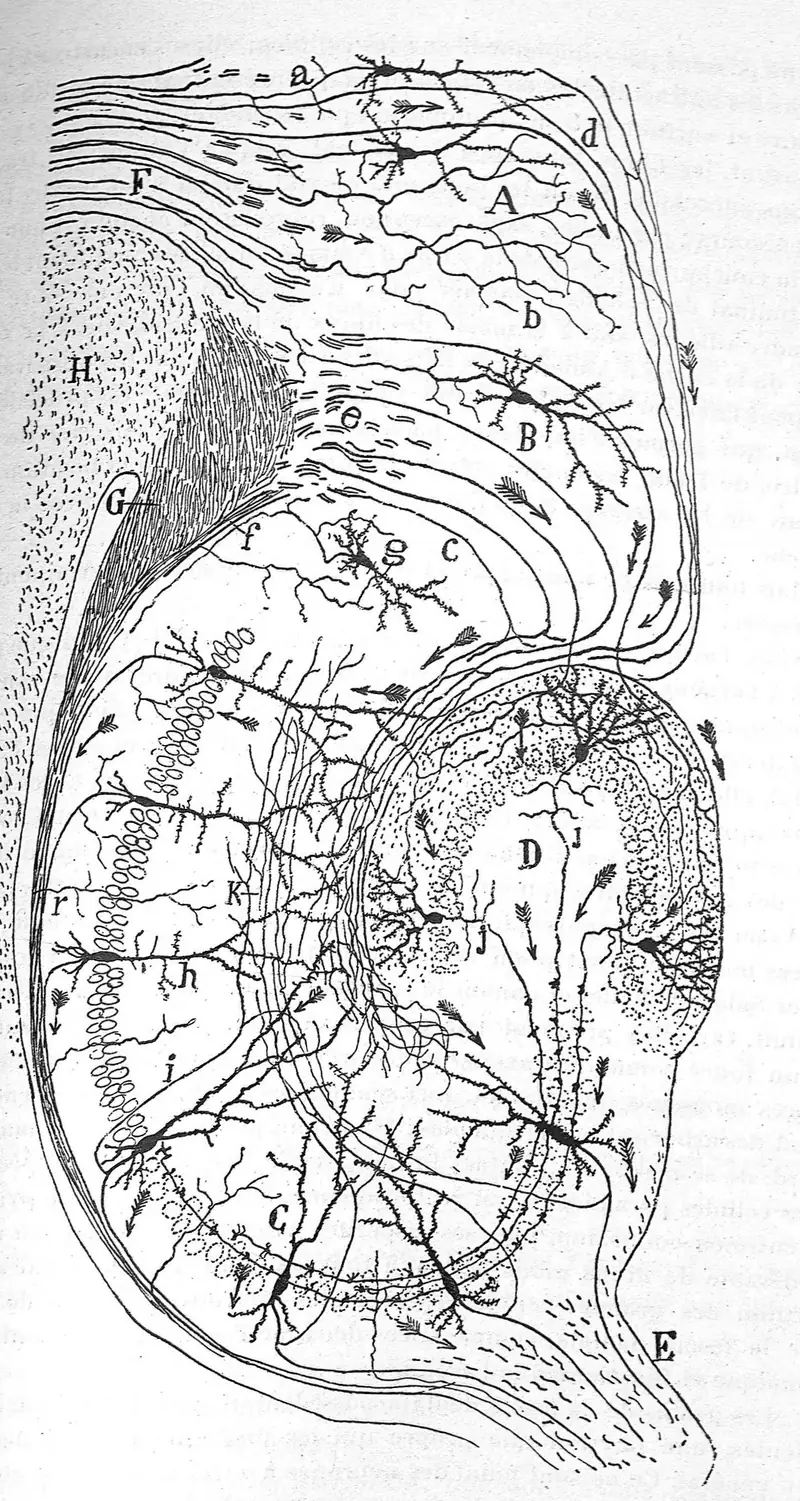
Cajal drew the circuits of the hippocampus by hand, a brain structure central to memory. Difficulties with memory and concentration have many possible causes, and assessment helps to tell them apart.
Santiago Ramón y Cajal, diagram of the connections of the hippocampus, in Histologie du système nerveux de l’homme et des vertébrés, vol. II, Paris, 1911, fig. 479. BIU Santé, Paris (Licence Ouverte). Public domain. Catalogue record (external site)
In brief
- Depression can affect memory enough to look like dementia.
- New difficulties, or ones that worsen or that others notice, justify an assessment.
- Mild cognitive impairment does not always progress; some people recover.
What they are
- Memory
- Attention
- Processing speed
- Language
- Executive functions
Complaints may be subjective, with normal tests, or a measurable deficit, mild or affecting independence.
Read more
Cognitive functions include memory, attention, processing speed, language and executive functions: planning, organising, deciding. Complaints may be subjective, with normal test results, or correspond to a measurable deficit, either mild or enough to interfere with independence.
Possible causes
- Depression, anxiety and insomnia: very common and treatable.
- Medicines (anticholinergic or sedative) and alcohol.
- Vitamin B12, thyroid and other metabolic causes.
- Cerebrovascular disease and vascular risk factors.
- Neurodegenerative diseases, such as Alzheimer’s (see dementia).
Read more
- depression, anxiety and insomnia, very common and treatable causes;
- medicines (for example, with anticholinergic or sedative effects) and alcohol;
- vitamin B12 deficiency, thyroid disorders and other metabolic causes;
- cerebrovascular disease and uncontrolled vascular risk factors;
- mild neurocognitive disorder and neurodegenerative diseases, such as Alzheimer's disease.
Depression, heart and cognition
Depression can affect attention and memory enough to look like dementia; treating mood tends to improve performance.
- Late-onset depression: a possible early sign of neurodegenerative disease; it justifies follow-up.
- Depression, cardiovascular disease and cognitive decline share mechanisms and risk factors.
Read more
Depression can markedly affect attention and memory, sometimes to the point of being mistaken for dementia; in these cases, performance tends to improve when mood is treated. In older people, late-onset depression may also be an early sign of neurodegenerative disease, which justifies follow-up.
Depression, cardiovascular disease and cognitive decline share mechanisms (inflammation, vascular changes, oxidative stress) and risk factors. This is the research field of Pedro Zuzarte.
Yes. Depression can reduce attention, memory and speed of thinking. Telling the two apart, while recognising that they can coexist, is one of the aims of the psychiatric assessment.
When to seek an assessment
Common forgetfulness
- Memory
- Occasionally forgetting names or objects
- Pace
- Some slowing
Warning sign
- Memory
- Repeatedly forgetting recent events
- Orientation
- Getting lost in familiar places
- Daily life
- Trouble with once-simple tasks
Read more
When difficulties are new or getting worse, are noticed by family or colleagues, interfere with work or everyday tasks, or come with changes in mood, sleep or behaviour.
Some slowing and occasionally forgetting names or objects are common. Repeatedly forgetting recent events, getting lost in familiar places or having difficulty with previously simple tasks warrants assessment.
What the assessment involves
- Talk
- History, with someone close
- Medication, mood and sleep
- Test
- Brief cognitive tests
- If needed
- Neuropsychological assessment
- Blood tests and brain imaging
- Coordination with neurology
Read more
It includes the clinical history, ideally with input from someone close, a review of medication, assessment of mood and sleep, and brief cognitive tests. Depending on the case, a more detailed neuropsychological assessment, blood tests and brain imaging may be requested. When indicated, follow-up is coordinated with neurology.
It depends on the history. They usually include cognitive tests, blood tests (for example vitamin B12 and thyroid function) and, in many cases, brain imaging. A full neuropsychological assessment is requested when brief tests are not enough.
Treatment and prevention
Treatable causes
Depression, anxiety, insomnia, vitamin deficiencies, inappropriate medication.
Protect cognition
Control blood pressure, diabetes, cholesterol; stay active; correct hearing.
If there is dementia
Specific medication and carer support.
of dementia cases may be linked to 14 modifiable risk factors across life.
Livingston et al., Lancet 2024.2
Read more
The first step is to address potentially reversible causes: depression, anxiety, insomnia, vitamin deficiencies, inappropriate medication. Controlling blood pressure, diabetes and cholesterol, physical activity, cognitive and social stimulation and correcting hearing loss all help protect cognitive health. A significant proportion of dementia cases is estimated to be associated with modifiable risk factors. When dementia is present, there are specific drug treatments, and support for carers is an essential part of the plan.
In numbers
Mild cognitive impairment: how many return to normal
- Studies in specialist clinics8%
- All studies18%
- Community studies25%
- Better-quality studies only26%
References
- National Institute for Health and Care Excellence. Dementia: assessment, management and support for people living with dementia and their carers [Internet]. NICE guideline NG97. London: NICE; 2018 [cited 2026 Nov 12]. Source (external site)
- Livingston G, Huntley J, Liu KY, Costafreda SG, Selbæk G, Alladi S, et al. Dementia prevention, intervention, and care: 2024 report of the Lancet standing Commission. Lancet. 2024;404(10452):572-628. doi:10.1016/S0140-6736(24)01296-0 DOI (external site)
- Canevelli M, Grande G, Lacorte E, Quarchioni E, Cesari M, Mariani C, et al. Spontaneous reversion of mild cognitive impairment to normal cognition: a systematic review of literature and meta-analysis. J Am Med Dir Assoc. 2016;17(10):943-8. doi:10.1016/j.jamda.2016.06.020 DOI (external site)
- Mitchell AJ, Shiri-Feshki M. Rate of progression of mild cognitive impairment to dementia – meta-analysis of 41 robust inception cohort studies. Acta Psychiatr Scand. 2009;119(4):252-65. doi:10.1111/j.1600-0447.2008.01326.x DOI (external site)
- Jessen F, Amariglio RE, van Boxtel M, Breteler M, Ceccaldi M, Chételat G, et al. A conceptual framework for research on subjective cognitive decline in preclinical Alzheimer's disease. Alzheimers Dement. 2014;10(6):844-52. doi:10.1016/j.jalz.2014.01.001 DOI (external site)
- Ruano L, Araújo N, Branco M, Barreto R, Moreira S, Pais R, et al. Prevalence and causes of cognitive impairment and dementia in a population-based cohort from Northern Portugal. Am J Alzheimers Dis Other Demen. 2019;34(1):49-56. doi:10.1177/1533317518813550 DOI (external site)
- Malek-Ahmadi M. Reversion from mild cognitive impairment to normal cognition: a meta-analysis. Alzheimer Dis Assoc Disord. 2016;30(4):324-30. doi:10.1097/WAD.0000000000000145 DOI (external site)
This page is for information only and does not replace an individual medical assessment.
Written and reviewed by Pedro Zuzarte, psychiatrist · Last reviewed:
A psychiatric assessment can be the first step.
If you are looking for psychedelic therapy, KETAMED is the clinic dedicated to this field.
Discover KETAMED (opens in a new tab)
Follow KETAMED: Instagram (opens in a new tab) · Facebook (opens in a new tab)