Obsessive-compulsive disorder: assessment and treatment
Obsessive-compulsive disorder (OCD) is characterised by intrusive thoughts that cause distress, the obsessions, and by repeated rituals to relieve them, the compulsions. It is common, often hidden out of shame, and effectively treatable: cognitive behavioural therapy with exposure and response prevention and, when indicated, medication.
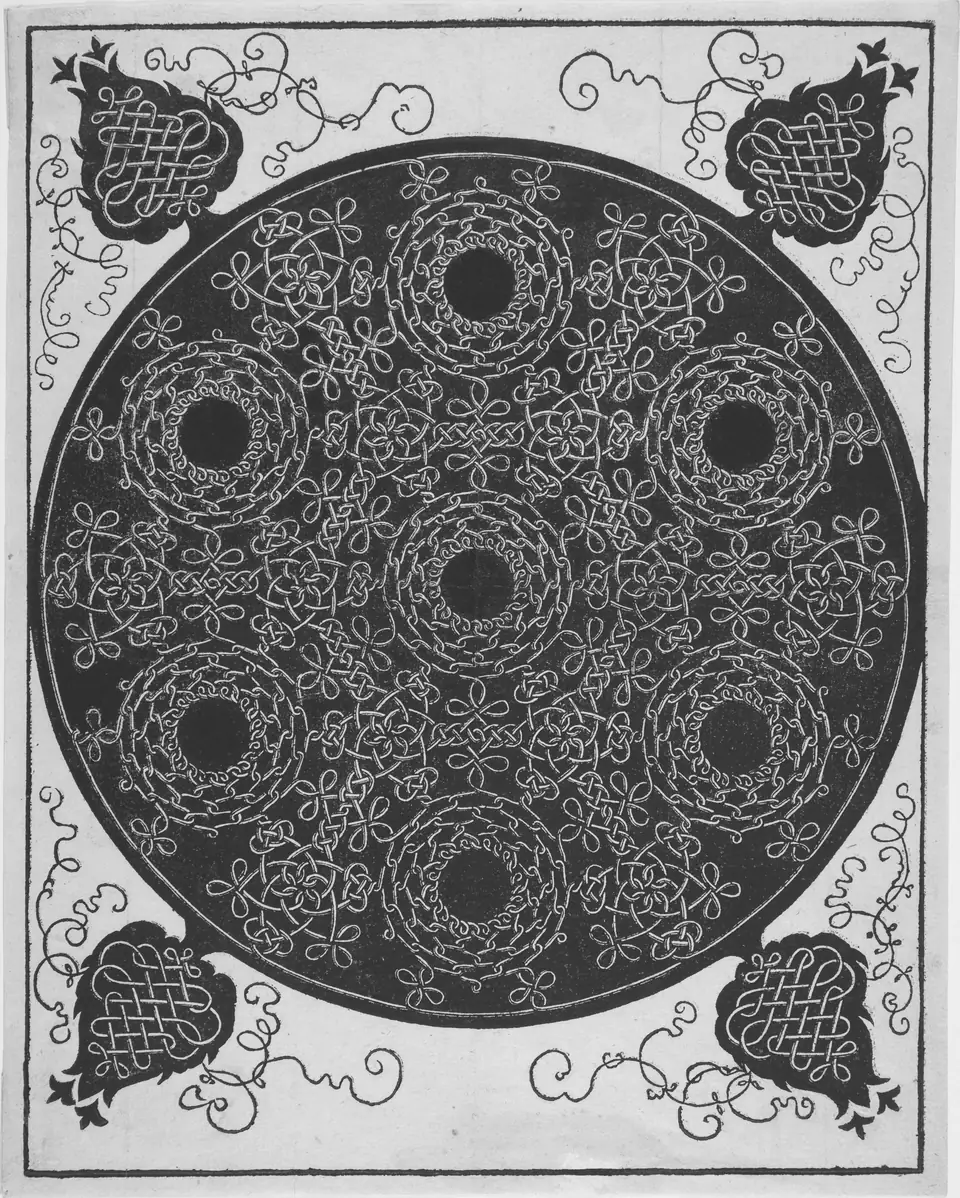
In Dürer’s “knots”, a single line interlaces without a break into a strict, symmetrical pattern. In obsessive-compulsive disorder, thoughts and rituals repeat in ways that are hard to stop; it is a treatable condition.
Albrecht Dürer, The Sixth Knot, before 1521. Woodcut. The Metropolitan Museum of Art, New York. Public domain. Catalogue record (external site)
In brief
- Intrusive thoughts are experienced as alien and do not mean desire or intention.
- The relief brought by rituals is temporary and ends up reinforcing the OCD cycle.
- With appropriate treatment, the symptoms often become mild and manageable.
What it is
- Obsession: an intrusive, unwanted thought.
- Anxiety or discomfort.
- Compulsion: a repeated ritual to relieve it.
- Temporary relief, which reinforces the cycle.
Temporary relief reinforces compulsions (Law and Boisseau, 2019).8
Read more
Obsessive-compulsive disorder is characterised by obsessions, compulsions or both. Obsessions are intrusive, unwanted thoughts, images or urges that cause anxiety or discomfort. Compulsions are repeated behaviours or mental acts performed to relieve that discomfort or prevent something feared.
The relief is temporary and reinforces the cycle: the more the obsession is answered with the ritual, the stronger it tends to become.
How it presents
- Fear of contamination, with repeated washing
- Persistent doubts, with repeated checking
- Order and symmetry, doing things “the right way”
- Intrusive thoughts experienced with great distress
- Mental rituals, such as counting
- Avoidance of what triggers the obsessions
Read more
- fear of contamination, with repeated washing or cleaning;
- persistent doubts, with repeated checking of doors, cookers or messages;
- a need for order, symmetry or doing things “the right way”;
- intrusive thoughts with aggressive, sexual or religious content, experienced with great distress;
- mental rituals, such as counting, praying or repeating phrases;
- avoidance of situations that trigger the obsessions.
Intrusive thoughts do not mean desire or intention. They are experienced precisely as alien and contrary to the person’s values.
Mental rituals include counting, praying or repeating phrases.
Almost everyone has occasional intrusive thoughts. In OCD, the thoughts are persistent, very distressing and lead to rituals or avoidance that take up time and limit life.
It is not perfectionism
Liking order is not OCD: in the disorder, rituals take up time, cause suffering and interfere with life.
Read more
Liking order or being demanding is not OCD. In the disorder, thoughts and rituals take up significant time, cause suffering and interfere with work, relationships or daily life.
Assessment
It characterises the obsessions and compulsions, the time they take, the degree of insight and their impact.
- It looks for depression, other anxiety disorders or tics.
- Specific scales measure severity and progress.
Read more
The assessment characterises the type of obsessions and compulsions, the time they take, the degree of insight and their impact, and looks for associated conditions such as depression, other anxiety disorders or tics. Specific scales help measure severity and follow the response to treatment.
Treatment
Psychotherapy
- Cognitive behavioural therapy with exposure and response prevention
- First line
Medication
- Some antidepressants
- Higher doses, slower response
Combination
- In more severe cases
- Usually the best option
Read more
- cognitive behavioural therapy with exposure and response prevention: the first-line psychological treatment;
- medication: some antidepressants are effective in OCD, often at higher doses and with a slower response than in depression;
- combination: in more severe cases, psychotherapy and medication together are usually the best option.
Psilocybin is being studied in OCD in clinical trials, with no approved clinical use; this research is summarised on psychedelic-assisted therapy.
With appropriate treatment, many people improve significantly. In many cases symptoms become mild and manageable; follow-up helps prevent relapse.
Research: psilocybin in clinical trials, no approved use (psychedelic-assisted therapy).
Related topics
In numbers
How many people have OCD: Portugal and ten countries
- Portugal, lifetime5.3%
- Portugal, past 12 months4.4%
- 10 countries, lifetime4.1%
- 10 countries, past 12 months3.0%
Frequently asked questions
How can I help a family member with OCD?
Avoid taking part in rituals or giving repeated reassurance, even when asked, and encourage an assessment. Family members can be involved in treatment.
References
- National Institute for Health and Care Excellence. Obsessive-compulsive disorder and body dysmorphic disorder: treatment [Internet]. Clinical guideline CG31. London: NICE; 2005 [last reviewed 2024 Jul 11; cited 2026 Nov 12]. Source (external site)
- Stein DJ, Costa DLC, Lochner C, Miguel EC, Reddy YCJ, Shavitt RG, et al. Obsessive-compulsive disorder. Nat Rev Dis Primers. 2019;5(1):52. doi:10.1038/s41572-019-0102-3 DOI (external site)
- Stein DJ, Ruscio AM, Altwaijri Y, Chiu WT, Sampson NA, Aguilar-Gaxiola S, et al. Obsessive-compulsive disorder in the World Mental Health surveys. BMC Med. 2025;23(1):416. doi:10.1186/s12916-025-04209-5 DOI (external site)
- Ruscio AM, Stein DJ, Chiu WT, Kessler RC. The epidemiology of obsessive-compulsive disorder in the National Comorbidity Survey Replication. Mol Psychiatry. 2010;15(1):53-63. doi:10.1038/mp.2008.94 DOI (external site)
- Fawcett EJ, Power H, Fawcett JM. Women are at greater risk of OCD than men: a meta-analytic review of OCD prevalence worldwide. J Clin Psychiatry. 2020;81(4):19r13085. doi:10.4088/JCP.19r13085 DOI (external site)
- Skapinakis P, Caldwell DM, Hollingworth W, Bryden P, Fineberg NA, Salkovskis P, et al. Pharmacological and psychotherapeutic interventions for management of obsessive-compulsive disorder in adults: a systematic review and network meta-analysis. Lancet Psychiatry. 2016;3(8):730-9. doi:10.1016/S2215-0366(16)30069-4 DOI (external site)
- Öst LG, Havnen A, Hansen B, Kvale G. Cognitive behavioral treatments of obsessive-compulsive disorder. A systematic review and meta-analysis of studies published 1993-2014. Clin Psychol Rev. 2015;40:156-69. doi:10.1016/j.cpr.2015.06.003 DOI (external site)
- Law C, Boisseau CL. Exposure and response prevention in the treatment of obsessive-compulsive disorder: current perspectives. Psychol Res Behav Manag. 2019;12:1167–1174. doi:10.2147/PRBM.S211117 DOI · PMC (full text)
This page is for information only and does not replace an individual medical assessment.
Written and reviewed by Pedro Zuzarte, psychiatrist · Last reviewed:
A psychiatric assessment can be the first step.
If you are looking for psychedelic therapy, KETAMED is the clinic dedicated to this field.
Discover KETAMED (opens in a new tab)
Follow KETAMED: Instagram (opens in a new tab) · Facebook (opens in a new tab)